 Skip to main content


 01274 442076


Pharmacy Pilot: How to Start With One Defined Neighbourhood Workstream
|
Getting your Trinity Audio player ready...
|
- What does a pharmacy pilot involve in practice?
- How do you choose which workstream to pilot?
- What should you measure before a pharmacy pilot starts?
- How do you know when a pilot is ready to expand?
A pharmacy pilot is easiest to evaluate when it tests one defined workstream and measures a baseline before launch. Post-discharge medicines coordination is a practical first choice, especially where it serves a priority already set in the local neighbourhood health plan. The cohort is countable, the end point is clear, and the workload effect is visible.
For PCN managers and commissioners, that focus matters. A narrow test produces interpretable data. A broad scheme produces activity and very little evidence.
Key takeaways
- One workstream: Choose a single pathway with a named owner, a defined patient cohort and a clear end point.
- Baseline first: Measure current performance for four to six weeks before you change anything.
- Balancing measures: Track workload, duplication and staff experience, not just activity.
- Honest claims: Existing evidence does not support promising reduced admissions from a small local pilot.
What does a pharmacy pilot involve in practice?

The neighbourhood health model aims to shift care closer to home. Each neighbourhood health plan then sets local priorities. Your pilot should serve one of them, not restate the programme.
A phased start works for most PCNs:
- Define the workstream and the eligible patient cohort.
- Collect baseline data before launch.
- Agree launch and expansion criteria with practices and the ICB.
- Test the pathway through small PDSA cycles.
- Review performance weekly on a run chart.
- Decide whether to expand, adapt or stop.
Need help turning a defined pharmacy workstream into a measurable pilot?
Discuss pharmacy pilot supportHow do you choose which workstream to pilot?
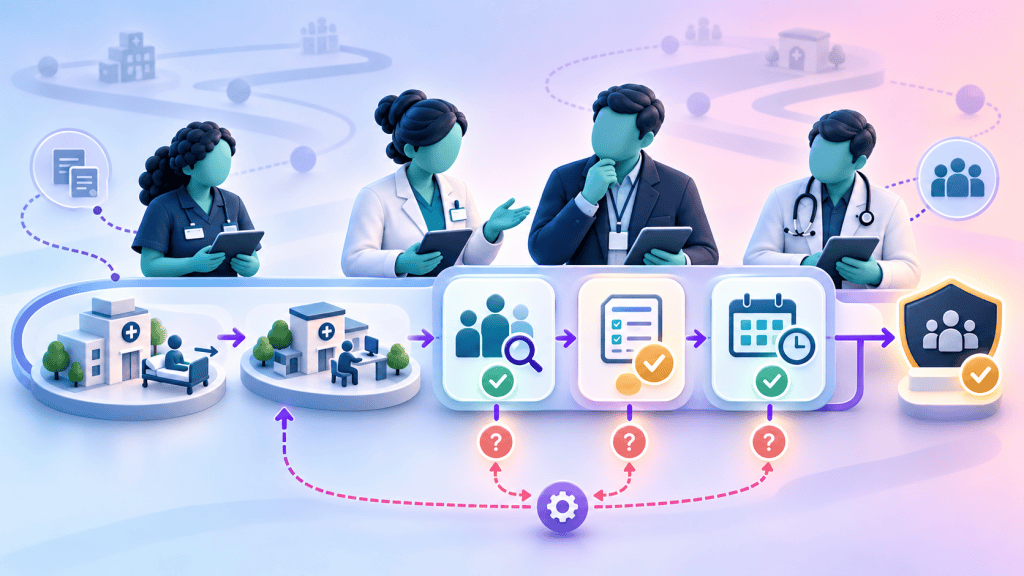
Pick a pathway where the problem is visible, the cohort is countable and the pharmacy team can act. Medicines reconciliation after hospital discharge meets all three tests.
Ask three questions. Can we list every eligible patient? Can we define what “done” looks like? Can one clinician deliver it within existing capacity? If any answer is no, narrow the pilot.

What should you measure before a pharmacy pilot starts?
Baseline data should cover at least four weeks, and longer where referrals are few. Record volume, timeliness and completion, not referral counts alone.
| Measure type | Example | Why it matters |
|---|---|---|
| Process measures | Discharges reconciled within seven days | Shows whether the pathway runs |
| Outcome measures | Patients with an accurate medicines list and a clear next step | Shows whether care improves |
| Balancing measures | Time per patient, duplicate contacts, GP queries | Detects workload shifting elsewhere |
Add patient reported experience measures and a short evaluation framework before go-live. Service evaluation NHS methods suit this kind of local testing. Use NICE quality standard QS120 for the reconciliation standard itself.
How do you know when a pilot is ready to expand?
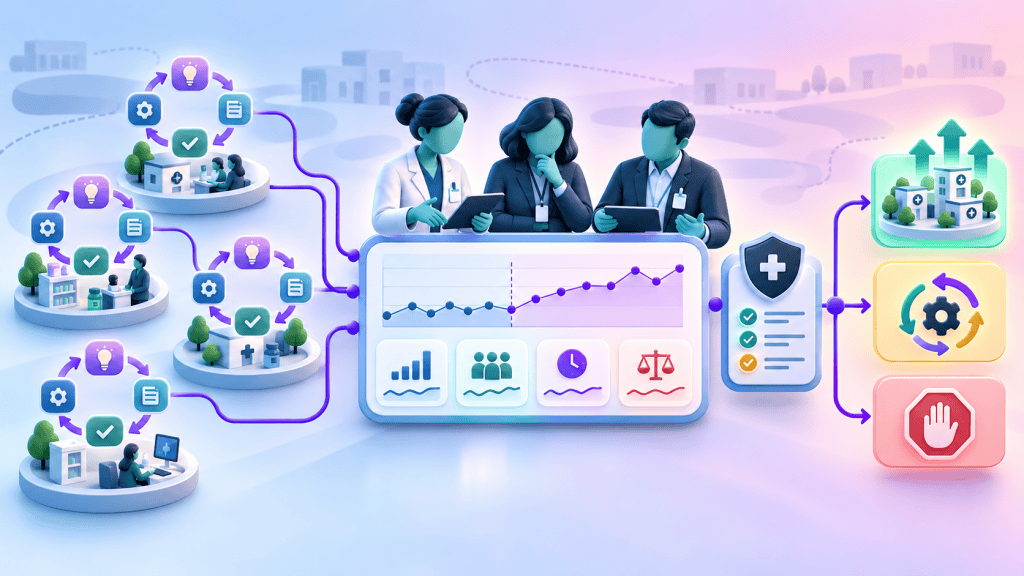
Set the thresholds before launch, and agree them with the practices and the ICB so they support the aims of the local neighbourhood health plan. A reasonable starting point: 90% of eligible patients offered the service, 80% completed within the target window, stable administration time, and no safety concerns.
Use a run chart to judge whether change is real. It separates genuine improvement from normal variation. Keep each PDSA cycle small and weekly.
Existing evidence does not justify promising fewer admissions from one local pilot. Report completed care, patient access and workload honestly. Wider admissions claims need larger designs, as our work on reducing medication-related hospital admissions explains.
Expert insight from Adeem Azhar, qualified Clinical Pharmacist and CEO
Pilots fail when they are judged on ambition rather than delivery. Define the baseline, agree the expansion criteria, and measure the work honestly. A modest pathway that reliably reaches every eligible patient teaches you more than a broad scheme nobody can evaluate.
Adeem Azhar, MPharm, IPres
Co-Founder and Chief Executive Officer – Core Prescribing Solutions
Qualified Clinical Pharmacist
FAQs
Turn one neighbourhood pharmacy priority into a governed, measurable pilot
Core Prescribing Solutions can support GP practices and PCNs to scope a defined pharmacy workstream, establish baseline measures and provide Clinical Pharmacist or Pharmacy Technician capacity for delivery. We can help build clear ownership, governance, review criteria and handover around the pilot so local teams can judge whether to expand, adapt or stop based on evidence.
Discuss your pharmacy pilot


