 Skip to main content


 01274 442076


Commissioning Pharmacy Support for a Neighbourhood health service: What Should the Specification Include?
|
Getting your Trinity Audio player ready...
|
- How do you build a pharmacy specification?
- What should an NHS service specification for pharmacy support include?
- How do you write acceptance criteria for service deliverables?
- Who owns clinical accountability and follow-up?
- How is the service monitored and evaluated?
An NHS service specification for pharmacy support defines the scope of work, the deliverables, the responsibilities and the acceptance criteria. It states what a provider must produce and how completion is judged. Most healthcare commissioning disputes come from two gaps: what finished work looks like, and who owns follow-up.
Key takeaways
- Define completion, not activity: Clear completion criteria turn “patients were reviewed” into evidence of signed-off work.
- Name the owner: Every service deliverable needs a named responsible role for follow-up.
- Separate national from local: The NHS Standard Contract sets the floor; local standards sit above it.
- Measure outcomes, not just counts: Pair activity metrics with clinical and outcome measures.
How do you build a pharmacy specification?
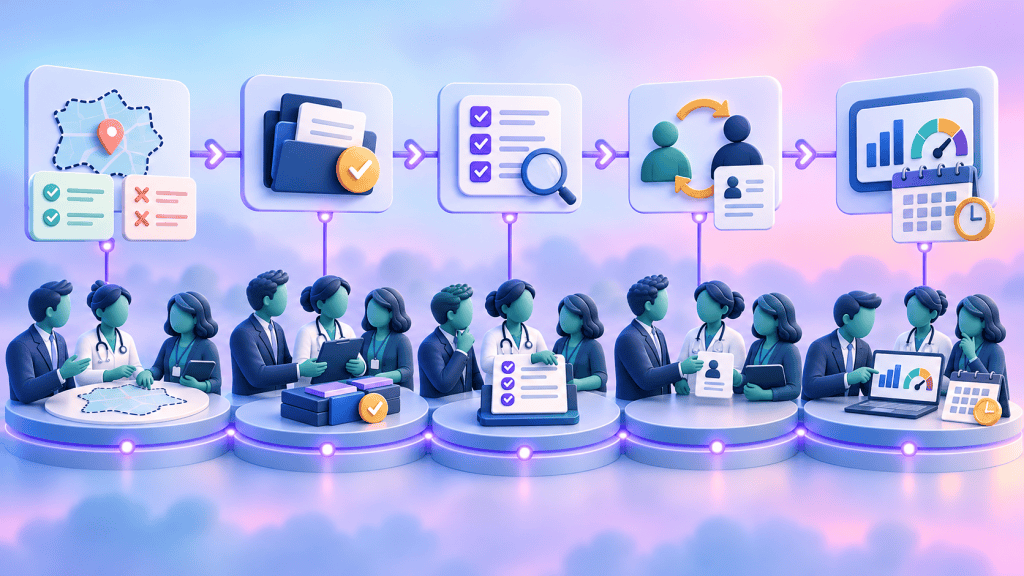
Five steps cover most of the drafting work.
- Define the scope of work.
- List the service deliverables.
- Write acceptance criteria for each deliverable.
- Assign responsibilities and follow-up ownership.
- Agree monitoring, escalation and review.
What should an NHS service specification for pharmacy support include?
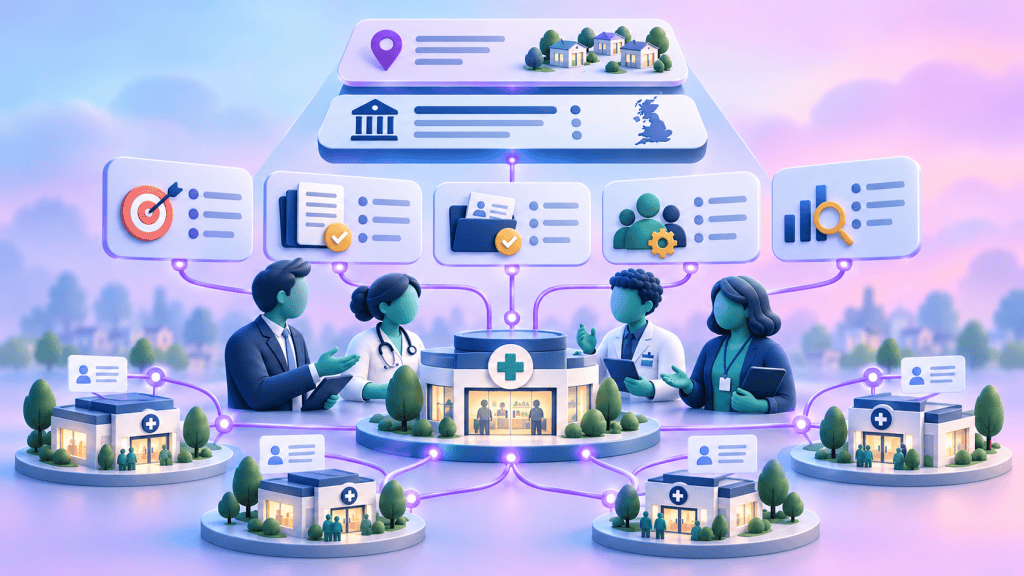
An NHS service specification should cover five areas: scope, deliverables, criteria, responsibilities and monitoring. National guidance sets the baseline; the NHS Standard Contract governs how those commitments are held.
| Component | What it defines |
|---|---|
| Scope of work | Included and excluded activities, eligibility and capacity |
| Service deliverables | What the provider must produce |
| Acceptance criteria | The evidence that each deliverable is complete |
| Responsibilities | Who owns decisions and follow-up |
| Monitoring | Reporting, service evaluation and review |
This matters more inside a neighbourhood health service, where providers work across several practices. The Integrated Neighbourhood Teams guide explains how those teams are structured.
Need help turning pharmacy requirements into a clear service specification?
Discuss pharmacy commissioning supportHow do you write acceptance criteria for service deliverables?
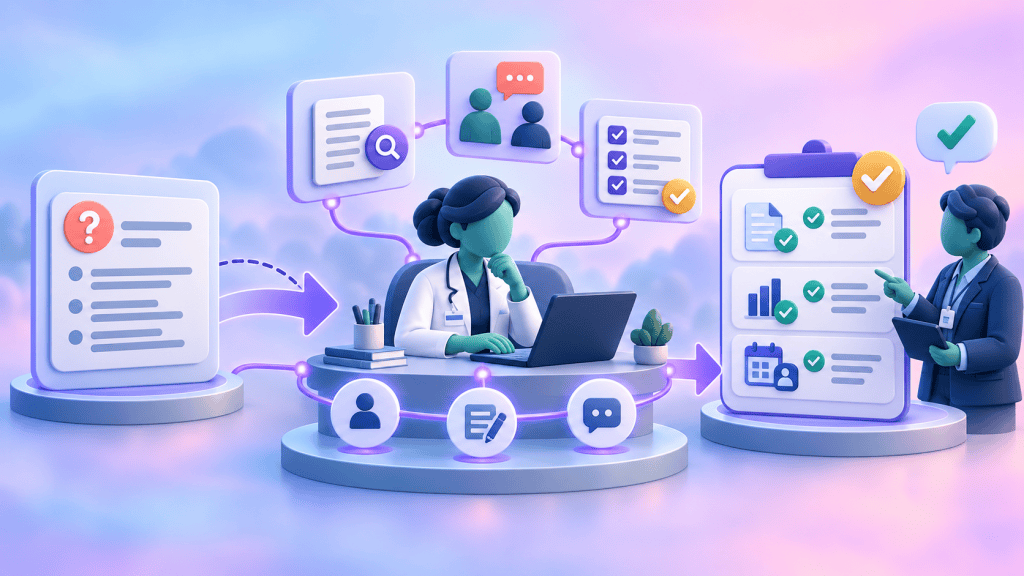
Acceptance criteria state the evidence required before a deliverable is accepted. They describe a finished, checked output, not a count of activity.
Vague deliverables create disputes. “Support structured medication reviews” is not testable. A stronger version states who completes the work, what is recorded and how completion is confirmed. A completed medicines review might need a documented clinical decision, a coded outcome and a follow-up action for the GP. NICE guidance on medicines optimisation supports this outcome-focused approach.
Write one to three criteria per deliverable, each specific enough to evidence.
Who owns clinical accountability and follow-up?
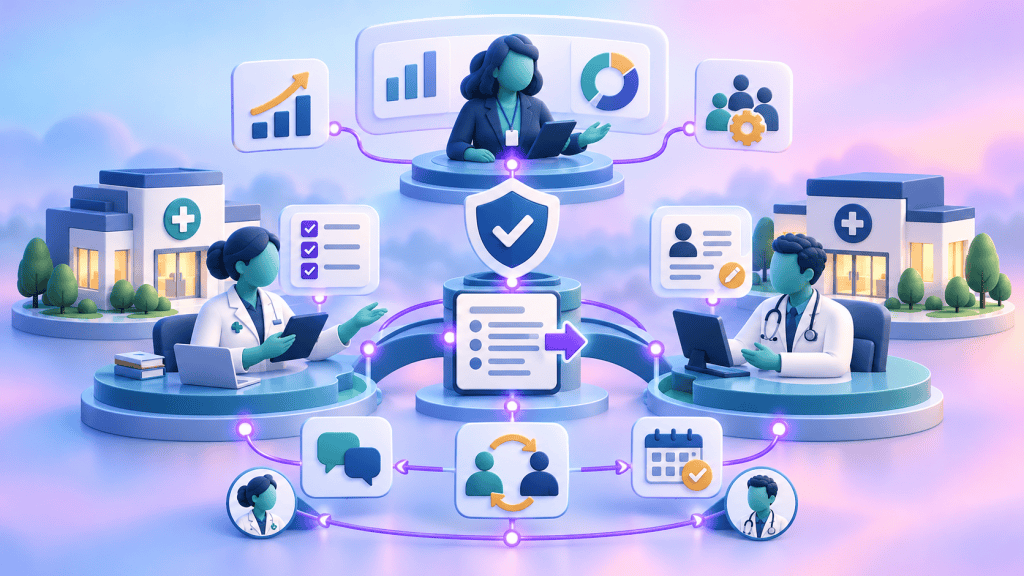
The provider owns the clinical decisions made by its own staff; the commissioner owns service-level oversight. The NHS service specification must name a responsible role for every follow-up action.
Ambiguity here carries the most risk. A pharmacist may complete a review, yet the practice still owns the patient record and any prescribing decision. State clearly which actions sit with the provider and which stay with the practice. Clinical supervision, case review and escalation routes belong in the contract, not in assumptions. Our clinical governance framework shows how these arrangements are usually structured.
Clinical accountability should be explicit, not implied. Put names against roles.
How is the service monitored and evaluated?
Monitor with a small, balanced dashboard, and review the NHS service specification at agreed intervals. Clear monitoring is the backbone of healthcare commissioning: it links payment and renewal to evidence. Contract monitoring should combine three levels:
- Activity: reviews completed and patients seen.
- Clinical: medicines stopped, started or changed, and safety issues resolved.
- Outcome measures: admissions avoided, adherence and patient-reported results.
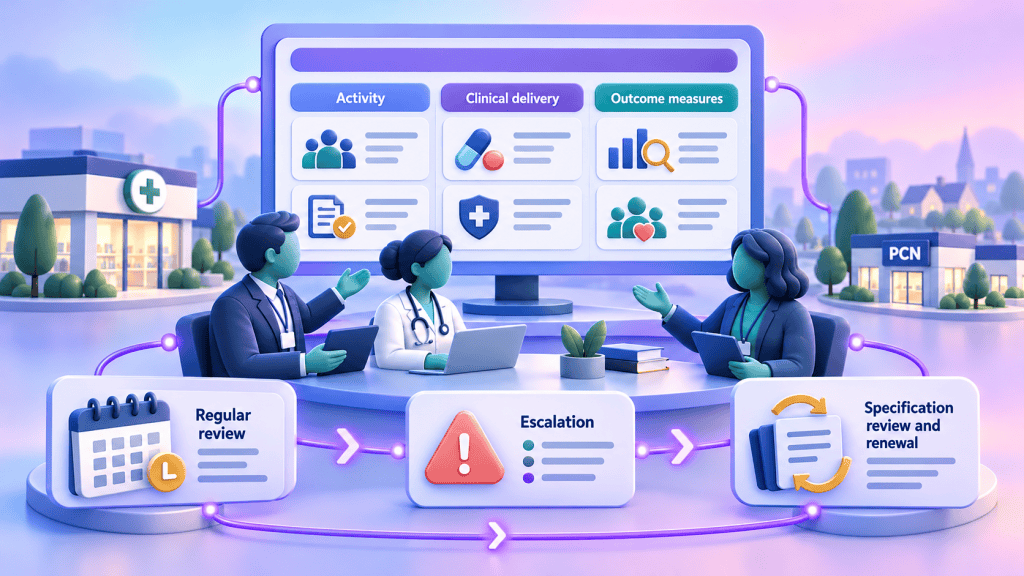
Key performance indicators describe delivery. Service evaluation asks whether the service changed anything. Keep the set proportionate, as too many indicators dilute attention.
Expert insight from Adeem Azhar, qualified Clinical Pharmacist and CEO
A specification is a promise with evidence attached. When scope, deliverables and criteria are clear, the provider knows what good looks like. Teams rarely struggle because of the wrong people; they struggle because of unclear expectations.
Adeem Azhar, MPharm, IPres
Co-Founder and Chief Executive Officer – Core Prescribing Solutions
Qualified Clinical Pharmacist
FAQs
Commission pharmacy support with clear scope, accountability and evidence
Core Prescribing Solutions can support GP practices, PCNs and neighbourhood services with Clinical Pharmacist and Pharmacy Technician capacity built around defined workstreams, deliverables and governance. We can help shape a practical delivery model with clear responsibilities, acceptance criteria, escalation routes and proportionate reporting so both commissioner and provider understand what successful delivery looks like.
Discuss your pharmacy service requirements


