 Skip to main content


 01274 442076


Clinical supervision agreement for PCN Pharmacists: What a Managed Support Arrangement Should Include
|
Getting your Trinity Audio player ready...
|
- What does national guidance expect from PCN pharmacist supervision?
- What should a clinical supervision agreement include?
- How should clinical case review and escalation work?
- Who is accountable for outsourced supervision?
- What should a PCN ask a provider?
A clinical supervision agreement in a PCN should be a written, operational document. It should name who supervises each Clinical Pharmacist, when support is available and how concerns are escalated. The 2026/27 Network Contract DES Part B guidance sets a monthly minimum. The test is whether supervision is documented, protected and assured.
Key Takeaways
- Each Clinical Pharmacist needs a supervision session at least monthly with a senior or advanced practice pharmacist.
- A named supervisor is not enough. Protected time, case review and escalation routes must be written down.
- Commissioning supervision does not transfer the practice’s duty to assure competence.
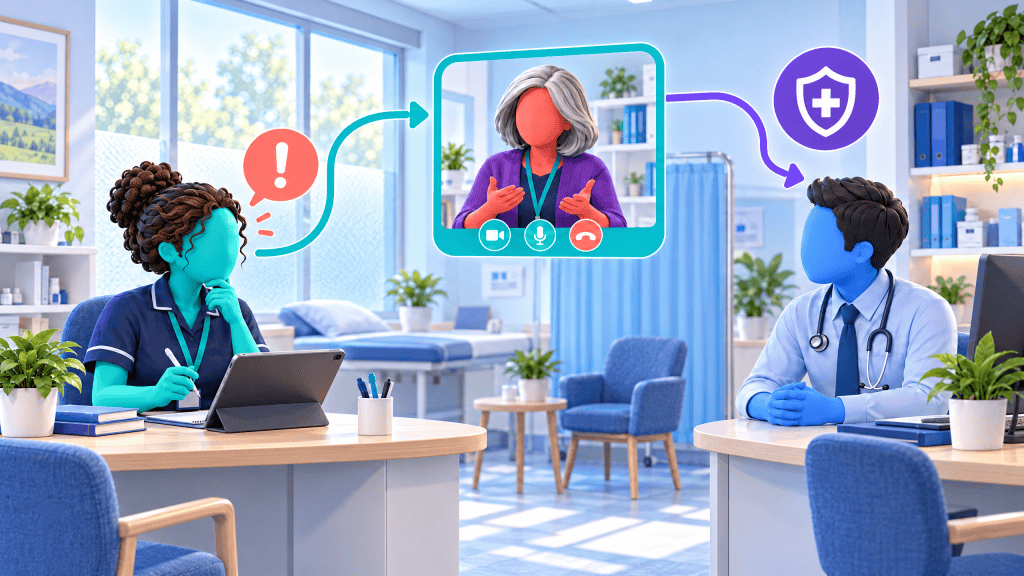
A working escalation
- A Clinical Pharmacist needs advice during a consultation.
- They contact the named supervisor or agreed deputy.
- If nobody responds in time, they pause and seek GP advice.
What does national guidance expect from PCN pharmacist supervision?

The 2026/27 Network Contract DES Part B guidance (sections 8.3.5-8.3.6) sets the baseline. Each Clinical Pharmacist should have at least one supervision session a month with a senior clinical or advanced practice pharmacist. The senior Clinical Pharmacist should have a session every three months with a GP supervisor. All should have access to an assigned GP clinical supervisor. Ratios should be no more than one senior to five.
NHS England’s broader supervision guidance for PCN multidisciplinary teams recommends monthly sessions for senior Clinical Pharmacists too, of at least an hour. That exceeds the DES minimum, so agree which you are meeting. The guidance also covers peer support and reflective practice. The DES also allows supervision from another PCN or secondary care, so external clinical pharmacy supervision is workable.
What should a clinical supervision agreement include?
A clinical supervision agreement should settle five points.
| Component | What must be explicit |
|---|---|
| Named supervisors | Senior Clinical Pharmacist, GP supervisor and deputies |
| Scope of practice | Approved activities, evidence of competence, how changes are agreed |
| Protected time | Frequency, duration, preparation and rearranged sessions |
| Case review | How cases are selected, discussed and documented |
| Escalation | Which concerns need same-day advice, and who receives them |
Protect supervision time in both diaries, alongside any agreed protected learning time, and set out each Clinical Pharmacist’s scope of practice. Evidence should reach the PCN: completed sessions, rearranged cancellations, agreed actions, unresolved concerns and themes from reflective practice, kept confidential.

Need managed Clinical Pharmacist supervision with clear governance and escalation?
Discuss clinical supervision supportHow should clinical case review and escalation work?

Clinical case review is where supervision produces action. A case based discussion should cover the reasoning, the decision and the follow-up, then assign actions to named people. Peer supervision adds perspectives that one-to-one review can miss. Reflective practice turns single cases into shared learning.
Escalation pathways need an owner and a fallback. A concern raised during a consultation may need advice before the next session. Agree who receives it, who provides backup and who confirms follow-up is complete.
Who is accountable for outsourced supervision?
Buying support does not hand over responsibility. The CQC expects practices to assure themselves that Clinical Pharmacists and Pharmacy Technicians are competent, supported and working within their scope of practice, even when they are not employed directly. The practice and Clinical Pharmacist must agree the range of prescribing activity and competence. Core Prescribing Solutions delivers managed clinical pharmacist support within defined scopes of practice, with clinical pharmacy supervision, governance and reporting built in.
What should a PCN ask a provider?
- Who supervises each Clinical Pharmacist, and who covers absence?
- How is clinical work reviewed against scope of practice, and who completes the actions?
- What evidence shows the arrangement is working?
Ask for named contacts, not role titles. A Clinical Pharmacist mentor supports development, while clinical supervision also provides structured oversight of practice. Training and development covers learning.
Expert insight from Adeem Azhar, qualified Clinical Pharmacist and CEO
Supervision protects patients best when it is specific. A PCN should be able to name the supervisor, the protected time, the case review route and the escalation contact before the service starts.
Adeem Azhar, MPharm, IPres
Co-Founder and Chief Executive Officer – Core Prescribing Solutions
Qualified Clinical Pharmacist
FAQs
Build a Clinical Pharmacist supervision arrangement your PCN can evidence
Core Prescribing Solutions can support PCNs with managed Clinical Pharmacist supervision built around named supervisors, protected time, defined scope of practice, structured case review and clear escalation routes. We can help make the arrangement practical and measurable while the practice retains its responsibility to assure competence and local clinical governance.
Discuss your supervision requirements


