Skip to main content


 01274 442076


Prescribing Explained: What Does Prescribing Mean in Healthcare?
|
Getting your Trinity Audio player ready...
|
- What does prescribing mean in healthcare?
- How does the prescribing process work?
- Who can prescribe medication in the UK?
- What is non-medical prescribing?
- Independent and supplementary prescribing
- Principles of safe and appropriate prescribing
Prescribing is the clinical decision to authorise a medicine for a named patient, with the prescriber accountable for that decision. For practices and PCNs, prescribing involves more than authorising a prescription. It shapes how medicines are chosen, explained, monitored and reviewed across the team.
Key takeaways
- Prescribing combines assessment, judgement, authorisation and follow-up. It is not simply issuing a prescription.
- Accountability stays with the individual prescriber, who must work within their competence and scope of practice.
- Workforce includes doctors, dentists and eligible registered professionals working through non-medical prescribing routes.
- Safety depends on a reliable process, patient involvement and timely review.
What does prescribing mean in healthcare?
Prescribing means deciding whether a medicine is appropriate for an individual patient, then authorising, explaining and monitoring that treatment. This prescribing definition holds in a GP consultation, a care home review or a pharmacist-led clinic. The prescribing meaning does not change with the setting.
How does the prescribing process work?

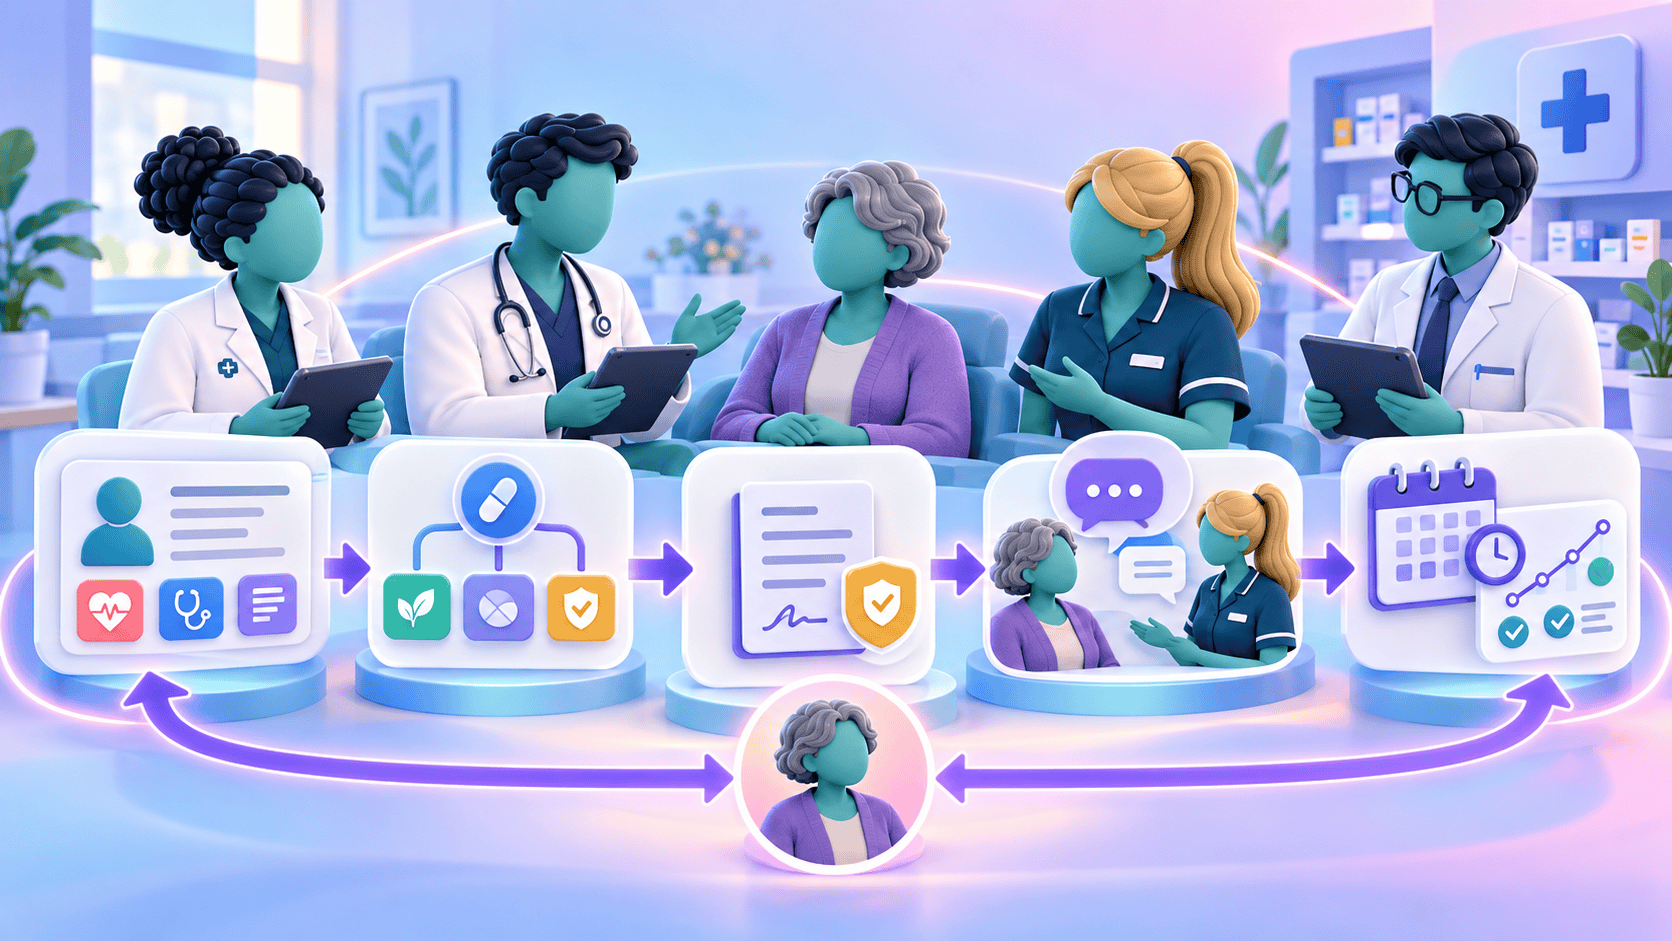
The prescribing process can be summarised in five connected steps. This is a practical structure, not an official standard. The prescribing process starts with the patient, not the product.
- Assess the patient, their condition, current medicines and relevant risks.
- Decide whether treatment is needed and which option suits the patient.
- Authorise the prescription, specifying medicine, dose, route, frequency and duration.
- Explain the intended benefit, risks and practical use to the patient or carer.
- Monitor outcomes, adverse effects and adherence, with a named person responsible for review and an agreed timescale.
Each step of the prescribing process depends on the one before it.
For example, a patient whose blood pressure stays above target might start on a single agent and be reviewed in four weeks. NICE guidance on medicines optimisation describes using medicines safely and effectively to achieve the best possible outcomes.
Who can prescribe medication in the UK?

Who can prescribe medication depends on registration, competence and scope of practice. Who can prescribe medication is settled by legislation and by the annotation on a professional’s register, not by local agreement. Doctors and dentists prescribe within their professional competence. Other professionals can qualify as independent prescribers: nurses, pharmacists, physiotherapists, podiatrists, therapeutic radiographers, paramedics and optometrists.
Not every profession with prescribing rights holds independent rights. Dietitians, for example, are supplementary prescribers. Taken together, these routes sit under non-medical prescribing. HCPC sets out the medicines and prescribing rights for each registered profession.
Need to expand prescribing capacity with clear clinical governance?
Discuss prescribing workforce supportWhat is non-medical prescribing?
Non-medical prescribing is the umbrella term for prescribing by eligible professionals who are not doctors or dentists. It covers independent prescribing and supplementary prescribing, and it has expanded access to treatment across chronic disease management, mental health and medicines reviews.
Independent prescribing sits at the widest end of that scope. Independent prescribing allows a qualified professional to assess a patient and prescribe within their competence. Independent prescribing in primary care strengthens access when roles, governance and clinical supervision are clear.
Social prescribing is different: it connects people with community support and does not involve authorising medicines.
Independent and supplementary prescribing

The two differ in how far the prescriber can act without another clinician’s involvement. Independent prescribing means deciding and authorising treatment on your own initiative. Independent prescribing is the more extensive of the two routes.
Supplementary prescribing is a voluntary partnership between a doctor or dentist and a supplementary prescriber. They work to a written, patient-specific clinical management plan, agreed with the patient’s knowledge and consent. The plan sets out the conditions treated, the medicines allowed, and any limits on dose or strength. Supplementary prescribing remains in use where a plan suits the patient’s care.
Working to another clinician’s plan is the essential difference between supplementary and independent prescribing.
Principles of safe and appropriate prescribing

The principles of prescribing help professionals make decisions that are clinically justified, patient-centred and proportionate to risk. Appropriate prescribing considers the patient’s needs, preferences, co-morbidities, existing medicines and the likely benefits and harms of treatment. Appropriate prescribing is a clinical judgement, not a formula.
Safe prescribing also requires accurate records, clear communication, monitoring and prompt action when a medicine stops helping. Safe prescribing depends on systems as much as individual judgement. The NICE medicines optimisation quality standard reinforces the need for patients to be involved in decisions about their medicines.
For PCNs, the principles of prescribing belong in clinical governance and routine review. Strong medicines optimisation helps teams use prescribing data, structured reviews and formulary decisions consistently. Clear medication safety processes give teams a route for handling high-risk medicines, incidents and shared learning.
Appropriate prescribing is not always about starting a medicine. It can mean adjusting treatment, stopping safely or supporting adherence. Audits, patient feedback and incident review all sharpen appropriate prescribing over time. Safe prescribing is a team activity, but each prescriber owns their own decisions.
Expert insight from Adeem Azhar, qualified Clinical Pharmacist and CEO
Good prescribing is not defined by how quickly a prescription is issued. It is defined by whether the decision is clinically sound, understood by the patient and reviewed when circumstances change. As responsibility expands across the workforce, PCNs need clear governance around that process.
Adeem Azhar, MPharm, IPres
Co-Founder and Chief Executive Officer – Core Prescribing Solutions
Qualified Clinical Pharmacist

FAQs
Build safe prescribing capacity across your PCN
Core Prescribing Solutions can support GP practices and PCNs with experienced Clinical Pharmacist capacity, medicines optimisation and prescribing-focused clinical delivery. We can help integrate prescribing roles into clear governance, review and escalation processes while keeping individual prescriber accountability and scope of competence central.
Discuss your prescribing priorities