 Skip to main content


 01274 442076


Methotrexate monitoring: What Can a Pharmacy Support Team Take Off a GP Practice’s Worklist?
|
Getting your Trinity Audio player ready...
|
- What do methotrexate monitoring guidelines require in primary care?
- What can a pharmacy support team do with DMARD bloods?
- How should a GP practice manage overdue methotrexate monitoring bloods?
- What happens after methotrexate monitoring is escalated?
- How can practices govern DMARD monitoring safely?
Methotrexate monitoring works best when a GP practice gives its Clinical Pharmacy team a defined process for overdue blood tests, missing results, follow-up and escalation. Delegating coordination does not remove the prescriber’s responsibility for making prescribing and delegation safe. Each professional must work within their competence, agreed role and local process.
Key takeaways
- Clear workflow: Pharmacy teams can progress overdue DMARD bloods through an agreed process.
- Safe escalation: Exceptions reach the appropriate clinician or specialist team promptly.
- Closed-loop assurance: An audit trail shows what is outstanding, accepted, resolved and still awaiting follow-up.
A practical workflow is:
- Define the cohort, shared-care requirements and escalation route.
- Search for DMARD bloods that are due, overdue, missing or incomplete.
- Reconcile results and issue protocol-led recalls where appropriate.
- Send exceptions for clinical assessment through the agreed pathway.
- Record actions, confirm handovers, set the next monitoring date and report open risk to the practice team.
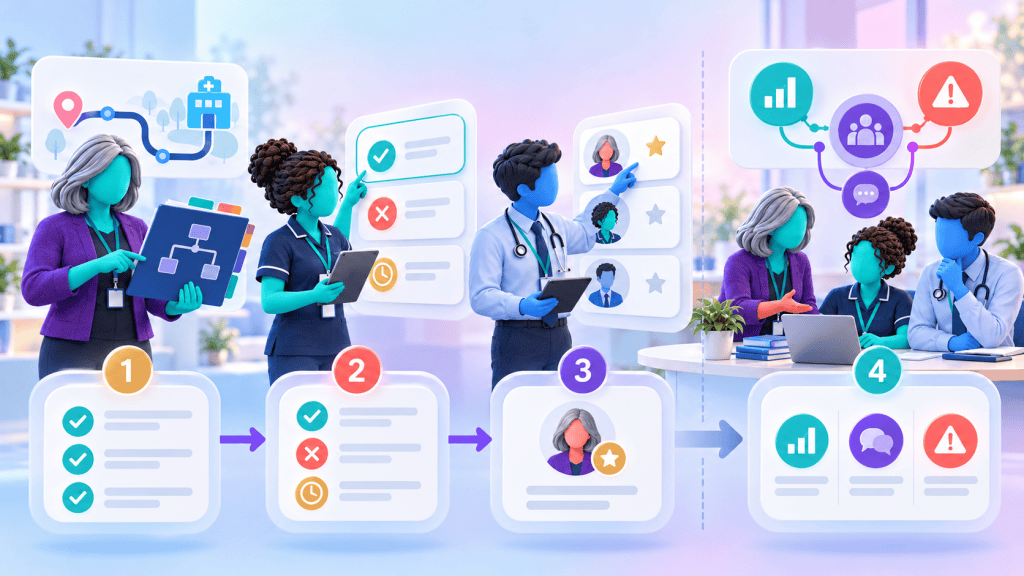
At weekly review, the team can:
- check methotrexate blood monitoring completion against the cohort list.
- review methotrexate blood monitoring exceptions before clinical huddles.
- flag methotrexate monitoring bloods that need escalation.
What do methotrexate monitoring guidelines require in primary care?
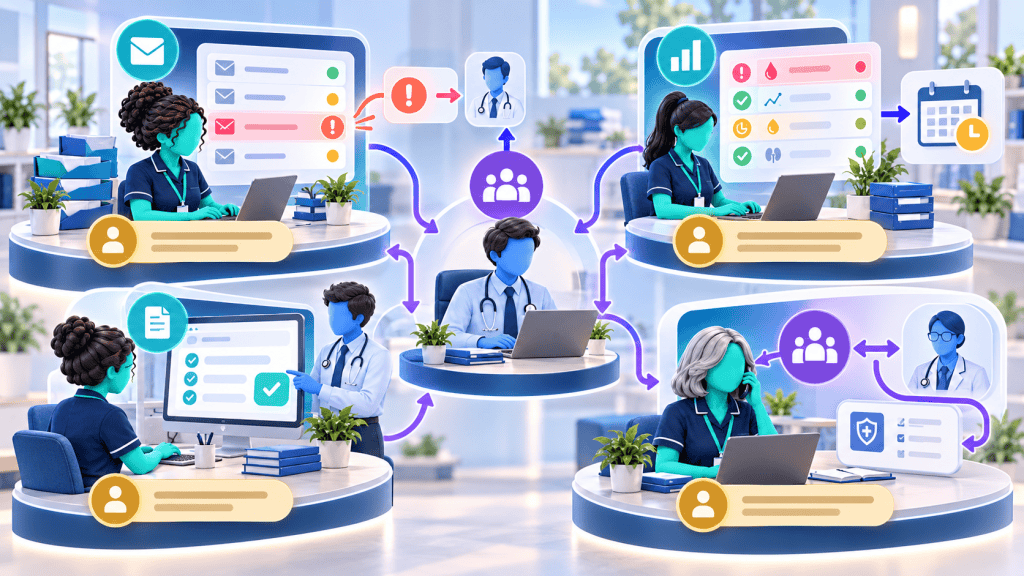
Methotrexate monitoring guidelines require an individual plan that follows the specialist’s shared-care arrangement and local protocol. NICE CKS states that DMARDs are initiated and initially monitored in secondary care. Once treatment is stable, primary care may continue prescribing and monitoring under shared care.
The 2025 BSR csDMARD guideline introduced a risk-adapted approach. It says risk factors for DMARD toxicity should be reviewed at least annually, with monitoring frequency adjusted to the risk identified. The NHS Specialist Pharmacy Service lists full blood count, liver function and renal function among the usual tests. Monitoring must still be individualised.
Need a governed process for overdue DMARD monitoring?
Discuss DMARD monitoring supportWhat can a pharmacy support team do with DMARD bloods?
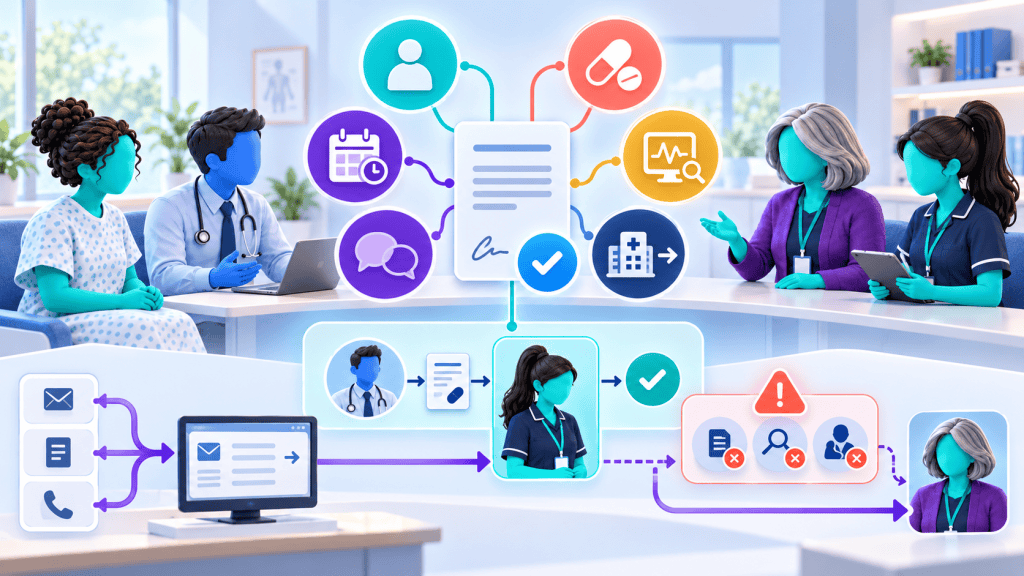
A Clinical Pharmacy team can identify patients whose DMARD bloods are due, reconcile absent results, contact patients under an approved process and maintain an exception list. This creates one reliable view of DMARD monitoring across the cohort. Pharmacy Technicians can support searches, recalls, data quality and tracking when this is within their competence and local governance.
A clinical pharmacist can review protocol-led exceptions, consider clinical context and escalate to the responsible prescriber or specialist team. The team should not alter treatment or take over specialist decisions without explicit authority.
How should a GP practice manage overdue methotrexate monitoring bloods?
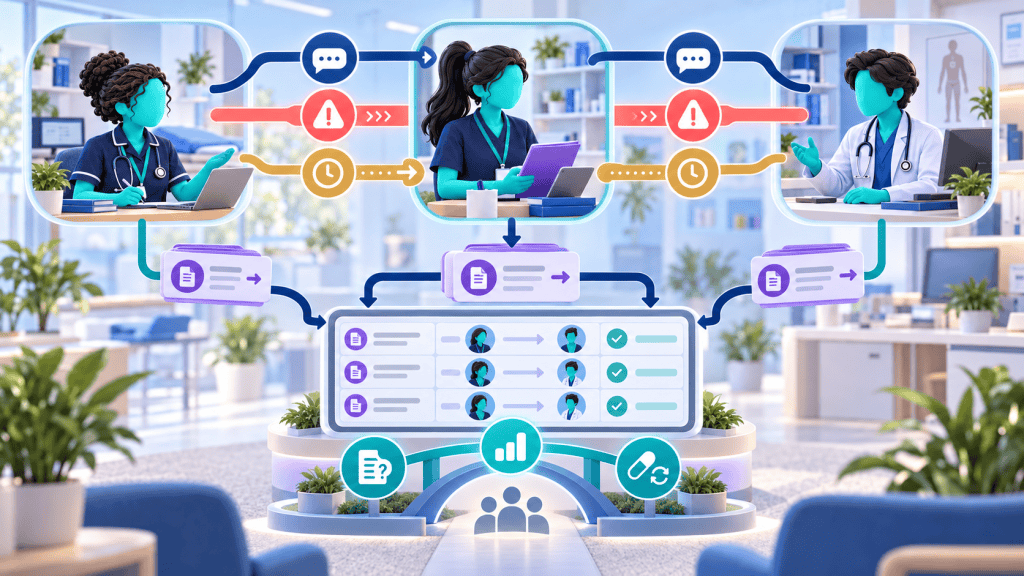
Overdue methotrexate monitoring bloods should enter one visible, owned exception process, not separate inboxes. Record the last result, planned test date, contact attempts, assigned reviewer and escalation status. This creates a practical bridge between individual recalls and wider high-risk medication monitoring.
For reliable methotrexate monitoring bloods, agree what happens when a result is absent, delayed or concerning. Changes in methotrexate liver function or renal function can affect the agreed plan. The pharmacy team should identify and escalate them under shared care, rather than apply a blanket instruction.
What happens after methotrexate monitoring is escalated?

Escalated is a task status, not a resolved outcome. Record who accepted the handover, the action requested, the due date and the named person who will follow up. Close the task only when the action is complete and the next monitoring date is recorded.
| Worked example | Closed-loop action |
|---|---|
| A hospital blood result is missing from the practice record. | A Pharmacy Technician obtains the result through the agreed route and records the source. |
| The result needs a clinical decision. | A competent clinician reviews it. Any repeat test or specialist advice is tracked to completion, with a named owner and next monitoring date. |
How can practices govern DMARD monitoring safely?
Safe DMARD monitoring needs a named owner, current protocol, defined roles and routine audit of open exceptions. DMARD monitoring guidelines should inform scheduled reviews. The shared-care arrangement and local policy should guide routine work. However, if they conflict with updated guidance or appear outdated, the responsible clinician should seek clarification from the specialist team and record the decision.
The GMC’s shared-care standards require agreement and effective communication between parties. They also say that prescribers remain responsible for the steps they take to ensure a prescription is appropriate, necessary and safe. This approach links monitoring work to medicines optimisation without blurring accountability.
FAQs
Turn DMARD monitoring into a visible, closed-loop workflow
Core Prescribing Solutions can support GP practices and PCNs with Clinical Pharmacist and Pharmacy Technician capacity for defined DMARD monitoring workflows. We can help with cohort searches, recalls, result reconciliation, exception tracking and appropriate clinical escalation within agreed shared-care arrangements, local protocols and professional scope.
Discuss your DMARD monitoring requirements


